Sharing clinical audit findings so people can act

21 Oct 2026

HQIP’s CEO, Chris Gush, explains how we share clinical audit findings, why it’s vital to improvement, and how everyone can help…

National clinical audit helps us see where care is working well and where it needs to improve. We want that evidence to be available to everyone who has an interest in it, particularly patients and the people responsible for delivering services. At HQIP, we publish findings and recommendations so they’re available for all to use, and work hard to get them to the people who can act on them. 

That includes being clear about findings that raise difficult questions. Differences in treatment, gaps in care, and inequalities in outcomes need to be understood. Patients should be able to see what the evidence says about their care, and those responsible for services should be able to explain how they are responding. 

The Government’s 10 Year Health Plan for England places transparency about the quality of care at the heart of NHS improvement. National clinical audit provides a robust foundation for that ambition. Our published findings help patients to ask informed questions, and give those responsible for services the evidence to identify priorities and track improvement. 

Our national clinical audit and outcome review reports are free to access through our online reports archive, alongside summaries and recommendations. We also publish a schedule of forthcoming reports, so people can see what is planned and arrange to receive regular updates. 

Our National Clinical Audit Benchmarking portal lets people explore published results by trust, hospital, unit or audit. Individual programmes provide further detail through their own websites and data platforms, including more recent results where available. 

We also have a responsibility to make recommendations useful. We work with audit teams and funders to reach a consensus on recommendations, considering what the evidence supports and who is best placed to act. Each recommendation makes clear what needs to improve and who is responsible for acting on it. 

HQIP’s approach has been informed by work on how national audit can better support improvement. In his June 2021 review, former HQIP Senior QI Lead Dr Ian Woolhouse proposed concise annual summaries with no more than five national recommendations, alongside public interactive results, more frequent feedback, and online resources to best support local improvement. The aim being to make the evidence easier to use in improving care. This work has informed how we structure reports and recommendations. 

The recommendations themselves are publicly available. Our reports and recommendations repository brings them together, helping organisations maintain oversight of what is being asked of services across different areas of care. 

We share new publications through website news announcements and a dedicated report bulletin, with further coverage in our regular monthly ebulletins. We send tailored information to NHS trust communications teams, professional bodies and national organisations, as well as clinical networks and charities with an interest in the subjects covered. 

We actively encourage colleagues and organisations to share through their own channels. We support this sharing through professional forums and social media, with follow-up posts drawing attention to individual reports. Further coverage in our newsletters and website articles keeps findings in view beyond publication day. 

We put effort into this because findings need to reach people with different responsibilities. Clinical teams need to understand what the results mean for their practice. Trust medical, nursing and multidisciplinary leaders, executive teams and boards need to consider the implications for quality and safety, and the action required within their organisation. 

Regional teams can use the evidence to identify shared challenges, and support learning between services. National organisations can use it to inform policy, standards and decisions about how care is organised. NHS England also circulates publication updates through its policy, clinical leadership, communications and regional quality networks. 

Our impact of data website area explains how this evidence supports safer care and addresses inequalities, alongside the contribution of patients and carers. We also publish programme impact reports on individual programme pages, including primary breast cancer, kidney cancer and maternity and perinatal care. These describe how programmes support improvement and complement their clinical findings and recommendations. 

Our current Breast Cancer Awareness Month campaign is a key example of how we work with the wider sector and patients to share our resources with those who need to see them. It brings together the primary and metastatic breast cancer audits, their published findings and recommendations, links to dashboards and articles explaining the work. It also includes a patient’s perspective, in both article and video formats, on the importance of data and listening to the people who use services. 

Our audit data also contributes to research that reaches audiences beyond the clinical audit community. In July 2025, research using PICANet data highlighted inequalities in outcomes for children admitted to intensive care. Published in The Lancet Child & Adolescent Health, the findings were shared publicly by Imperial College London and HQIP. The Guardian also covered the research. This helps bring important questions about the quality and fairness of care into wider public discussion. 

Open reporting also means explaining results carefully. Readers need to know what period the data covers, how comparisons have been made and where there are limitations. Our published clinical findings and recommendations are open to everyone, while the underlying patient information remains subject to safeguards that protect confidentiality. 

I welcome interest in our work from patients, healthcare professionals and the media. National clinical audit provides a basis for asking informed questions about care and holding services to account. We want people to read the findings, discuss the recommendations and use them to support improvement. 

I would encourage anyone interested in healthcare quality to explore HQIP reports and sign up for publication updates. Within services, the findings should inform improvement plans and board discussions, with clear responsibility for responding to recommendations. By working together, we can support patients to see what has changed as a result.

Sharing national clinical audit

How clinical audit is helping the NHS improve the entire breast cancer pathway

1 Oct 2026

October 2026 is Breast Cancer Awareness Month – find out more about HQIP’s work on this topic in our NEW breast cancer care hub

For everyone diagnosed with breast cancer, the journey from diagnosis through treatment and beyond is life changing. Each patient’s experience is unique, but breast cancer services aim to provide timely, high-quality care to people that responds to their individual circumstances, and the type of breast cancer they have.

Delivering on this aim is a significant challenge for the NHS. While advances in diagnostic processes and treatment continue to improve outcomes for many with breast cancer, it is important that we understand whether those improvements are delivering results for all patients. This is where clinical audit plays a vital role as one of the NHS’ key improvement tools, and helps health providers to understand what parts of the care pathway are working well – and what are not – and ensure improvements benefit patients at every stage of their experience.

As the NHS works to deliver the ambitions set out in the NHS 10 Year Health Plan for England and the National Cancer Plan for England, understanding how care is delivered becomes increasingly important. National cancer audits, including the National Audit of Primary Breast Cancer (NAoPri) and the National Audit of Metastatic Breast Cancer (NAoMe), delivered as part of the National Cancer Audit Collaborating Centre (NATCAN) commissioned by Healthcare Quality Improvement Partnership (HQIP), produce robust evidence that helps services understand how breast cancer care is being delivered across England and Wales. Publicly available information is provided for each breast unit, at a regional level (Cancer Alliance in England) and national level, enabling the benchmarking of performance, the identification of unwarranted variation, and the prioritisation of actions where it will have the greatest impact.

“A breast cancer diagnosis comes as a shock to most and is accompanied by a myriad of decisions with long term consequences that require careful consideration during what can be a very turbulent time. The equitable presentation of information about all treatment options and their universal availability across the UK is paramount to patient satisfaction.

The clinical data routinely recorded about every patient care episode in the NHS provides the UK audit teams with the unique ability to compare the care provided by different Cancer Alliances and identify areas of variability; they are then uniquely positioned to analyse the cause and subsequently improve patient care. The opportunity for patient advocates to sit on the NAoPri and NAoMe panels and provide feedback on the data output ensures it is considered with patients interests at the heart of discussions with those delivering care at the front line.

As an example of this, one of the primary targets of the NAoPri is to improve the rates of, and equitable access to, immediate breast reconstruction. From a patient perspective this has to be balanced against the need to make such a big decision at the point of diagnosis and therefore requires the care pathway to provide sufficient clinic time for full and open discussions about patient values, lifestyle and expectations along with an evidence-based presentation of what treatments are clinically appropriate.”

Sam Brunsden, Patient Representative/Research Advisor Flat Friends

Breast cancer: Understanding care from diagnosis onwards

Both the NAoPri and NAoMe audits have highlighted the importance of Triple Diagnostic Assessment (TDA), combining clinical examination, imaging, and tissue sampling at the initial consultation. This approach supports timely and accurate diagnosis, helping to reduce uncertainty for patients. The National Cancer Plan identifies earlier and more effective diagnosis as a critical factor in improving outcomes, making the audit’s focus on diagnostic pathways particularly important. NAoPri’s latest State of the Nation report, published September 2026, showed that in England and Wales between 2021 and 2023, only 68% of patients diagnosed with early breast cancer had a TDA, although this was a small improvement from 66% in the previous period (2020-2022). There was also marked variation between breast units; and so this metric will remain an audit focus.

The support provided by clinical nurse specialists (CNS) during the diagnostic process is invaluable and recognised as such by all major clinical guidelines. Among patients for whom CNS information was available, 94% had CNS contact – close to the expectation in NICE Quality Standard 12 statement 6 that all patients with breast cancer should be assigned a named CNS or other specialist key worker.

Breast cancer treatment is also increasingly personalised. Surgery, drug therapy, and radiotherapy all play important roles, depending on an individual’s diagnosis and preferences. The audits are helping services assess whether patients have equitable access to these treatment options and identify where practice is changing over time.

Amongst the many treatment options available, the audits have focused recently on the use of neo-adjuvant chemotherapy and uptake of immediate breast reconstruction. There has been increased use of neoadjuvant chemotherapy over the last decade among groups for whom it is recommended, a treatment approach that can reduce tumour size before surgery and inform subsequent treatment. In the latest audit period, 56% of people with stage 2 to 3A triple-negative or HER2-positive breast cancer received treatment before surgery.

Access to immediate breast reconstruction (IBR) following mastectomy is beginning to recover following the disruption caused by the COVID-19 pandemic. IBR refers to reconstruction of the breast at the same time as mastectomy. For women undergoing mastectomy, it is an important surgical option that provides potential psychological benefits. Just over a quarter of women undergoing mastectomy had an immediate reconstruction (2021-23).

The audit also found that around one in six people required a further operation following breast-conserving surgery to achieve clear margins of disease. The rate was 27% for ductal carcinoma in situ, compared with the NAoPri target of 15%, and 15% for invasive disease, compared with a target of 10%. On this measure, as well as many others within the audit, organisational rates ranged significantly, giving services a clear national benchmark against which to review their practice. Identifying unwarranted variation and supporting improvement in this way is a core function of clinical audit. While differences in patient populations will always influence treatment decisions, understanding why outcomes and practices vary can help organisations learn from one another and improve care across the system.

What outcomes can tell us

In England and Wales, 3-year all-cause survival and breast cancer-specific survival among people diagnosed with stage 1 to 3A invasive breast cancer between 2022 and 2023 were 92% and 98%, respectively. Notably, the audit has recently implemented a process to identify providers which are outliers for 3-year survival.

Metastatic breast cancer: Bringing new visibility to this stage of the pathway

The National Audit of Metastatic Breast Cancer (NAoMe) is the only NATCAN audit dedicated to assessing the care of patients with metastatic disease. Patients either present with metastatic disease (de novo) or metastatic disease diagnosed following previous diagnosis of primary breast cancer (recurrent).

“For those of us living with metastatic breast cancer, data is far more than numbers. It is a vital tool for identifying inequalities in care, addressing unwarranted variation and ensuring that every patient has access to the best possible treatment and support, wherever they live. By turning data into meaningful improvements in services, we can work towards what patients want most: a better quality of life and improved survival outcomes.”

Carla Whitbread, NAoME Patient Representative with MBC Lived Experience 

One of the five quality improvement goals adopted by the NAoMe is to “improve the movement of patients through the care pathway”. National and international guidelines recommend that a Multidisciplinary Team (MDT) considers the management options for people with metastatic breast cancer, because it supports coordinated, individualised treatment planning and helps ensure care is consistent with clinical guidelines, including NICE guidance. The NAoMe 2026 State of the Nation report highlights that during 2021-2023, 81% of patients with de novo disease across England and Wales were discussed in an MDT meeting (against the audit target of 90%).

There are also encouraging signs in access to specialist support and treatment. Recorded CNS contact in England increased from 59% to 62% (2020-2022 vs 2021-2023), while the proportion of eligible patients receiving HER2-targeted treatment increased from 72% to 75% – modest but important movements.

Similar to NAoPri, care variation was commonly identified but, again, this is where the audit working together with the wider cancer care sector can make a difference. By shining a light on metastatic breast cancer care, their work helps ensure that improvement efforts extend beyond diagnosis and initial treatment, including areas that have historically received less attention.

One of the most significant developments in breast cancer care is the major focus on identifying when a person has metastatic recurrence. Understanding when this occurs is essential for evaluating treatment effectiveness, planning services, and improving long-term outcomes. NAoMe’s work has already produced practical guidance for hospital-level data entry, helped identify approximately 6,000 additional people through the exploration of treatment and radiotherapy datasets, and brought together seven UK organisations through a data improvement group. By working with National Disease Registration Service (NDRS) and other partners in strengthening the recording of recurrence, the audits are contributing to a more complete picture than has previously been possible – aligning with national ambitions to strengthen the use of data to improve service planning.

Turning insight into improvement: Further opportunities for the future

The growing availability and use of national cancer data creates an important opportunity to make the picture of breast cancer care increasingly complete, timely, and useful. Continued work to improve the completeness and consistency of routinely collected NHS data will strengthen further the insights provided by NAoPri and NAoMe, enabling services to make fairer comparisons and understand patients’ experiences more fully.

Provider-level dashboards, targeted feedback, and practical improvement resources are already helping NHS organisations review their results and identify priorities for action. Alongside these resources, specific quality improvement initiatives are helping to address areas highlighted by the audit findings, and continued, proactive focus on this work will be important in supporting further progress. As an example of this improvement, NAoPri’s work on immediate breast reconstruction supports organisations to understand their results and explore potential barriers relating to service configuration, capacity, referral pathways, and shared decision-making. NAoMe’s work on the recording of breast cancer recurrence is similarly combining practical guidance for local teams with national collaboration and the exploration of additional data sources.

This work aligns closely with national priorities in England and Wales, to improve the use of data, reduce unwarranted variation, and translate evidence into practice. National clinical audit is not simply a means of measuring care, but an important part of the infrastructure for improving it.

As data and quality improvement approaches continue to develop, NAoPri and NAoMe are well placed to bring together evidence, clinical expertise, patient perspectives, and practical support for local action, helping the NHS understand whether advances in diagnosis and treatment are reaching patients consistently and equitably. For everyone affected by breast cancer, the goal is simple: that wherever they live, whatever their circumstances, and wherever they are treated, they can have confidence in receiving the best possible care throughout their journey.

Further resources from HQIP

My breast cancer story: From heartbreak to hope

1 Oct 2026

As part of Breast Cancer Awareness Month, patient representative, advocate and author of ‘Why Me? My Fight for Life From Heartbreak to Hope’, Sharon-Ann, talks to HQIP about her breast cancer journey, sharing her thoughts about the value of data and patient involvement in the design and delivery of breast cancer care. Watch the video, or scroll down to read the article…

“Although my breast cancer was diagnosed in 2020, my cancer journey started five years earlier. At that time, for around a year, I had been repeatedly misdiagnosed. Eventually, through the NHS Choose and Book system, I chose to go to St George’s in Tooting, where they identified what had previously been missed, and I was diagnosed with multiple myeloma and associated cardiac amyloid. One hospital sadly failed me, while another saved my life. During my subsequent treatment, my heart became severely damaged, leading to stage 2 heart failure and, at one point I was given just six months to live.

By 2020, my multiple myeloma was in remission but, during lockdown, I found a lump. In fact, I was prompted to check by Breast Cancer Awareness Month, and so I went to my GP. They referred me to a hospital within the necessary time frame and that was quickly followed by a lumpectomy, chemotherapy and radiotherapy. Thankfully, since entering the breast cancer pathway, everything has gone extremely well, and I’m pleased to say that I’m now cancer free. They took into consideration my background and heart failure. I felt as if my patient care and worries were noted pretty much throughout, and the overall care has been extremely good; the treatment was rapid. 

From patient to patient advocate  

As a result of my multiple myeloma, I wrote a book in 2018, to talk about the effects of misdiagnosis, as well as other factors such as (for me, at that time) issues around support given by a clinical consultant versus a Clinical Nurse Specialist (CNS). However, since then, I have contributed regularly to nurse training at St George’s over several years; and I have subsequently seen first-hand how things have changed for the better (when accompanying someone else who had been diagnosed with lymphoma on a hospital visit). With my multiple myeloma, the whole experience was very clinical; but 11 years on, the change was amazing. The consultant explained everything, and then she gave us time with the CNS for as long as we needed, in a separate room.

Since writing my book, I have acted as a patient advocate, raised significant funds for Macmillan Cancer Support, and worked as an insights panellist for a number of organisations. In 2025, I started a Community Interest Company (CIC), Heartbreak to Hope, which grew out of my book and my own experiences. Through the CIC, I support people affected by serious illness, loss and major life changes, with a focus on early awareness, prevention and health inequalities. 

The importance of patient voice AND data 

I believe that data is extremely important in improving patient care and outcomes, because it shows what’s working and what isn’t. But, speaking to patients tells you something else; it tells you what it feels like. I think that it’s so important to have both, in order to improve care. I feel like I can be the person behind the numbers. 

Personally, I’ve always questioned pretty much everything that I’ve been told. I was advised to have a mastectomy and, for me, it wasn’t what I wanted. I was supported in that decision by my consultants, and we went down a different pathway. While the doctors can give you medical advice, as patients, we know ourselves. It’s important that the patient is involved in their own healthcare.

As a Black woman, I’m also very conscious of inequalities in healthcare, with people having spoken to me about differences in their experiences of care. I think this is another area where data is important, because it can help us see where those differences exist. But we need to use that information, alongside what patients are telling us, to make changes.  

Treat the person, not the condition 

With my breast cancer care, I had multiple additional issues that needed to be taken into consideration. As mentioned, I was in remission for multiple myeloma, and had severe heart failure. So, for a long period, I was navigating different cancer teams as well as the cardiac team. And they don’t necessarily fit into any one pathway. Therefore, I think we need to look at the whole person, because they are often juggling so many different things. Again, we need the data to steer treatment; but it needs to be more joined up. 

Breast Cancer Awareness Month: early detection saves lives 

Finally, I’d like to encourage everyone to know what is normal for their breasts, and check themselves regularly this Breast Cancer Awareness Month, and every month! Finding a problem early can mean prompt diagnosis and treatment (one of the slogans for 2026 is Early detection saves lives). That was certainly the case with my breast cancer. I saw something on social media during the campaign that reminded me that we need to check ourselves, and that’s how I found the lump. It’s so important to use these awareness events to encourage people to check themselves. I do it on a monthly basis, but October is a good opportunity to remind everyone. If I didn’t find the lump when I did, I probably wouldn’t be here today. Self-detection does indeed save lives.

Further resources

Finding the missing millions: Driving improvements in cardiovascular disease prevention

30 Sep 2026

In light of World Heart Day on 29 September 2026, we revisit the CVD Modern Service Framework, together with CVDPREVENT (National Audit of Cardiovascular Disease Prevention in Primary Care)

Following the publication of the Government’s Cardiovascular Disease (CVD) Modern Service Framework (MSF) in July 2026, CVDPREVENT (commissioned in part by HQIP*), reflects on how it supports the audit’s core aim of “finding the missing millions who don’t yet know they are at risk” (as their Clinical Lead, Dr Peter Green, puts it). In other words, how will the CVD Framework work in tandem with programmes like audits and the wider sector to prevent ‘heart disease’, and reduce related complications and deaths over the next decade? 

A single national ambition 

The Modern Service Framework has one main clear and measurable ambition: to reduce premature deaths from heart disease and stroke among people under 75 by 25% within ten years. To achieve this, it sets out a goal of reaching people who are most likely to experience heart attacks and strokes before these events occur. The Framework adopts a cardiovascular-kidney-metabolic (CVKM) approach, which recognises the close connection between cardiovascular disease, kidney disease and metabolic conditions such as diabetes. Rather than addressing these conditions separately, it seeks to improve prevention, diagnosis and treatment across the whole pathway. 

Aligning CVDPREVENT with the Framework’s priorities 

The MSF’s initial focus is on driving improvements in twelve priority areas over the next three years. Each priority has a baseline, a three-year target and a ten-year target. Such clear goals support clear metrics for CVDPREVENT, and so they are aligning their work to relevant priorities in the Framework. To enable ICBs and other healthcare planners to work toward one consistent set of national ambitions, CVDPREVENT is adopting the MSF’s ambitions where they supersede the audit’s previous targets. In the case of some priorities, their work is able to already evidence progress: 

Framework priority CVDPREVENT indicator 
Priority 3: SGLT2 inhibitors The new CVDP001VCVKM indicator supports monitoring of appropriate SGLT2 inhibitor use as part of a broader CVKM approach 
Priority 4: Hypertension treatment to target CVDP007HYP measures treatment to target among people with hypertension who do not have established cardiovascular disease 
Priority 5: Lipid optimisation CVDP008CHOL supports the assessment of lipid management among people without established CVD 
Priority 7: Blood pressure and cholesterol optimisation For people who already have cardiovascular disease, the framework will use: CVDP010HYP, a new hypertension indicator CVDP012CHOL, which measures cholesterol treatment to target 
Priority 8: Four-pillar therapy for heart failure The new CVDP004HF indicator supports monitoring of four-pillar therapy for people with heart failure with reduced ejection fraction, commonly known as HFrEF 

Case finding – identifying the missing millions 

The audit’s indicators also support the measurement of two further CVD MSF priority areas: smoking cessation (priority 1) and CVRM case-finding (priority 2). In relation to the latter, the scale of case-finding required is significant. CVDPREVENT’s data indicate that more than one million people across England have a recorded marker that may suggest undiagnosed hypertension, chronic kidney disease (CKD) or diabetes. In March 2026, 1.86% of the registered population (942,504 people) had a single blood pressure reading of 140/90mmHg or above but no GP-recorded hypertension. A further 0.39% had their last two eGFRs (measure of kidney function) below 60ml/min/1.73m², meeting the diagnostic criteria, but no GP record of CKD. Finally, 0.044% had their last two HbA1c records at 48mmol/mol or above, meeting the diagnostic criteria, but no GP record of diabetes. Over 1.1 million people remain in these potential missed diagnosis groups. Identifying these people is central to the ambition of “finding the missing millions”. Earlier diagnosis provides opportunities to manage risk factors before someone experiences a heart attack, stroke or other serious complication. Case-finding is therefore not simply about adding diagnoses to patient records. It is about connecting people to appropriate services, and saving and improving lives. Millions of lives, in fact. 

Liz Corteville, Quality Improvement Lead at CVDPREVENT, adds: “What this scale tells us is that the opportunity to save lives is already sitting in GP records, right now. Our job at CVDPREVENT is to make that visible and actionable, through the Quality Improvement Data Packs, the Data & Improvement Tool and targeted educational outreach, so finding these million-plus people isn’t an abstract national ambition but something a practice or PCN can genuinely work through, quarter by quarter.” 

Making variation visible 

One of CVDPREVENT’s greatest strengths lies in making variation visible. As of March 2026, cholesterol treatment of patients with identified CVD target stood at 52.96% nationally, however achievement varied significantly by ethnicity (ranging from 40.8% in the Black ethnic group to 56.9% in the Asian ethnic group1). Insights like this enable ICBs, GP practices and other healthcare providers to target support, rather than treat CVD prevention uniformly.  

The audit’s insights are also extremely valuable in aligning resources with local need. For example, in Hampshire and the Isle of Wight, where CVDPREVENT data have been used to compare local performance with other areas of England, and target support accordingly. As a result, between March 2022 to September 2025, the ICB reported considerable improvements: 

  • Additional 55,000 people without established CVD being identified as being at high risk of developing it.
  • Additional 62,500 people being diagnosed with hypertension
  • Additional 70,000 people having their blood pressure treated to target
  • Additional 47,000 people at high risk of CVD starting lipid-lowering treatment 

Also, between June 2024 and September 2025, a further 5,000 people with known CVD had their cholesterol treated to target.

Looking forward  

The Modern Service Framework signals that further indicators aligned to CVDPREVENT’S work are likely to follow. As outlined above, the audit has already introduced new baseline indicators in the current reporting round, including measures relating to CVKM risk and heart failure. Over time, this should expand the programme’s treatment-to-target role from the priorities it already covers to fuller CVKM reporting.  

While CVDPREVENT will be the principal source of information on the Framework’s primary care priorities, it will not cover every aspect. Priorities concerned with acute hospital care and rehabilitation are likely to remain within the remit of other national audits, such as stroke. This reflects the broader value of the MSF: bringing together information from different parts of the health system around a shared set of outcomes and ambitions. This vision is consistent with the aspirations of wider national healthcare strategy. As the first Modern Service Framework to be published following the NHS 10 Year Health Plan, the CVD MSF’s importance extends beyond preventing, and improving care for, cardiovascular disease (acutely important though that is). Its publication, and subsequent delivery, offers a blueprint for improving treatment, and reducing premature deaths from, a spectrum of conditions, by aligning national strategy and targets with improvement initiatives, including national clinical audits. CVDPREVENT, whose reporting now feeds into the NHS Oversight Framework, is a forerunner of this approach. 

And, as for the “missing millions” living with undiagnosed hypertension, chronic kidney disease, diabetes or other cardiovascular risk factors? By combining clear strategic ambitions with robust national and local intelligence, we stand a much better chance of identifying who they are – and, importantly, saving and improving their lives. If the ambition of the Modern Service Framework is realised, they will no longer be missing; they will be found, supported and given the opportunity to live long and healthy lives. 

1 CVDPREVENT Data & Improvement Tool 

*About CVDPREVENT 

CVDPREVENT is commissioned by HQIP as part of the National Clinical Audit and Patient Outcomes Programme (NCAPOP), and delivered by NHS England, NHS Arden and Greater East Midlands Commissioning Support Unit (AGEM CSU) and the NHS Benchmarking Network (NHSBN), which leads the audit’s reporting and quality improvement workstream. It aims to support professionally-led quality improvement in primary care for the prevention of cardiovascular disease (CVD) in England, and has reported on a quarterly basis since data collection began in 2019/20.  

Further information 

CVD MSF

From data to safer care: The role of stroke audit in improving quality of care

7 Sep 2026

Published in partnership with Patient Safety Learning.

Ensuring patients receive the right care at the right time is one of the most important patient safety challenges facing the NHS, not least in stroke care where every minute matters. Rapid recognition, assessment, timely access to reperfusion therapy and effective specialist rehabilitation can mean the difference between a good recovery and lifelong disability.

That challenge is becoming more significant. Stroke remains a leading cause of death and disability, with more than 92,000 people admitted to hospital with stroke across England, Wales and Northern Ireland during the period from April 2024 to March 2025. High-quality care for these patients requires coordination across the entire pathway, from prevention and emergency response through to specialist hospital care, rehabilitation and long-term support.

With this year’s World Patient Safety Day focusing on safe care for noncommunicable diseases, this article reflects on the critical role that national clinical audit plays in supporting safer care, with a focus on stroke. The Sentinel Stroke National Audit Programme (SSNAP), led by King’s College London and commissioned by the Healthcare Quality Improvement Partnership (HQIP), demonstrates how evidence-based standards developed from national guidelines can help drive quality improvement across a complex healthcare pathway.

Driving improvement through data and innovation

SSNAP measures the quality and organisation of stroke care across England, Wales and Northern Ireland. By collecting and analysing data across the patient journey, it gives a detailed understanding of where services are performing well and where care can be strengthened. This aligns closely with the ambitions of the NHS 10 Year Health Plan, which emphasises the importance of using data and innovation to improve outcomes, reduce inequalities and support continuous quality improvement.

While audit provides the evidence and insight to support improvement, progress in stroke care depends on the collective efforts of multidisciplinary stroke teams, patients and their representatives, commissioners, researchers, charities and many others working across the pathway. Clinical audit forms a vital part of that infrastructure, with routine, tangible, clinically meaningful data measured against evidence-based standards to support quality improvement and patient safety.

This role has become even more essential following publication of the new Cardiovascular Disease Modern Service Framework, which sets out a 10-year ambition to reduce premature deaths from heart disease and stroke through earlier prevention, access to organised stroke care and rehabilitation, supported by innovation and adoption of evidence-based interventions in order to reduce health inequalities. National clinical audit provides insight and stimulates enquiry to identify reasons for variation and priorities for quality improvement.

The impact of this approach can already be seen across stroke services. Many of the most encouraging developments reflect the same themes of data and digital transformation that underpin the NHS’s shift from analogue to digital healthcare. Advances in imaging, AI decision-support technologies and data-driven pathways are helping more patients access time-critical treatments and improving outcomes.

For example, SSNAP’s latest State of the Nation report, which covers April 2024 to March 2025 (2024/25), shows that access to brain imaging continues to improve. The proportion of patients receiving brain imaging within 20 minutes of hospital arrival increased from 26.5% April 2023 to March 2024 (2023/24) to 28.3% in 2024/25, and the proportion receiving imaging within one hour increased from 59.5% to 61.4%. These improvements matter because timely imaging is crucial to select patients for targeted effective hyper-acute treatments. Hospitals need to perform all the necessary imagery at the same time, as well as using artificial intelligence tools to support clinical decision-making, to improve the delivery of reperfusion therapy and provide patients the best opportunity to recover.

Encouragingly, access to hyper-acute treatments such as thrombolysis and thrombectomy has also improved. The proportion of patients receiving thrombolysis increased from 11.6% to 12.2%, while thrombectomy rates increased from 3.9% to 4.4% (2023/24 vs 2024/25). Both treatments can significantly reduce disability when provided promptly. Use of national audit data has stimulated quality improvement for thrombolysis rates in several stroke services and progress has been made for a number of time-metrics for thrombectomy, although growth of thrombectomy rates still requires further attention.

Further, there has been notable progress in the treatment of intracerebral haemorrhage, where the proportion of eligible patients receiving an appropriate hyper-acute intervention within one hour of hospital arrival increased from 24.9% to 32.0%, an important patient safety improvement for a group of patients who often experience poorer outcomes. These advances demonstrate how audit can support innovation by identifying where new approaches are succeeding and where further improvement is needed.

Progress is not universal

While there are many reasons for optimism, there are also areas where progress has been more difficult. Perhaps the most striking example is the growing delay between stroke onset and hospital arrival. In 2024/25, the median time from stroke onset to arrival at hospital increased to 4 hours and 11 minutes, compared with 2 hours and 25 minutes a decade earlier (2013/14). The reasons are complex and may include public awareness and recognition of symptoms, ambulance pressures and wider system factors. There is a continuing need for sustained public education to enhance awareness of stroke symptoms, faster ambulance recognition and triage through innovation such as pre-hospital video assessment.

Access to specialist stroke care, which is the most effective intervention to reduce disability and mortality from a population level, also remains challenging. Less than half of patients (46.5%) were directly admitted to a stroke unit within four hours of hospital arrival, while the proportion spending at least 90% of their hospital stay on a specialist stroke unit fell slightly to 74.0%.

Importantly, acknowledging these trends, through national clinical audit, is the first step in finding solutions in order to reverse them, and illustrates why continuous measurement and quality improvement is essential. National clinical audit helps identify where delays and barriers occur, enabling local systems to focus improvement efforts where they are likely to have the greatest impact on patient outcomes and safety.

Understanding variation: a nuanced picture

One of the most important messages from the recently published SSNAP Atlas of Variation Report is that variation is not necessarily unwarranted. Too often, variation is assumed to indicate poor performance. In reality, differences between areas may reflect population characteristics, levels of deprivation, geography, service configuration, patient preferences, access to specialist services or differences in local health needs.

For commissioners, this is an important distinction. The purpose of examining variation is not to assign blame. Rather, it is to understand why differences exist and to identify opportunities for learning and more equitable care. It is also important that organisations responsible for commissioning stroke care compare their performance with both peer organisations and the national average. These comparisons can highlight areas of good practice, encourage shared learning and support ongoing quality improvement across the stroke pathway.

This approach is echoed in the recently published Cardiovascular Disease Modern Service Framework, which argues that “success is judged on closing the gap, not just the average”. For commissioners, providers and clinical teams, this highlights the importance of looking beyond headline performance measures to understand where inequalities persist, where variation may reflect different population needs and where targeted efforts could have the greatest impact.

The Atlas provides numerous examples of variation. Nationally, 25.9% of patients with known atrial fibrillation were not receiving anticoagulation before their stroke, with a range regionally from 9.8% to 32.3% – a key opportunity for prevention. There is also substantial variation in thrombolysis rates and other aspects of care across different populations and regions.

The report also points to significant future challenges. Stroke admissions in England are projected to increase by 28.8% over the next decade, with considerable variation between areas (ranging between 7.1% in NHS Derby and Derbyshire to 61.5% in NHS North Central London). Understanding local patterns of demand and care delivery will become increasingly important for planning future services, and national clinical audit provides insight to support that planning.

Looking beyond hospital care

“One of our key goals is to make sure more patients can access the full specialist stroke pathway, as this leads to better recovery and outcomes.” SSNAP State of the Nation Report 2025

The NHS 10 Year Health Plan sets out a shift from hospital-based care towards more integrated community care, and stroke services are already moving in this direction. SSNAP reports continued growth in access to specialist community rehabilitation services following discharge from hospital. The proportion of patients discharged to a stroke/neurology-specific community rehabilitation service has increased to two-thirds of all discharges: 66.6% in 2024/25. Over a third (23.1%) of these patients were transferred to a combined stroke/neurology specific Early Supported Discharge and Community rehabilitation team. This reflects the ongoing commitment to implementation of the national service model for an integrated community stroke service across England.

However, the audit also highlights areas where further progress is needed once patients leave hospital. The proportion of patients receiving a 6-month review after stroke has continued to decline since 2019/20, falling to 35.1% in 2024/25 (38.8% in 2023/24). Long-term support after stroke is critical to patient outcomes and quality of life. As care increasingly shifts into community settings, robust data will remain help ensure services provide safe and equitable care.

Looking beyond recovery and rehabilitation, the NHS’s shift from sickness to prevention is equally relevant. Findings from the Atlas of Variation demonstrate opportunities to improve management of risk factors such as atrial fibrillation and hypertension before stroke occurs. Preventing strokes in the first place will be as important to improving population health as advances in acute treatment.

Evidence that leads to improvement

Overall, the story of stroke care is one of continued improvement, with SSNAP demonstrating how national clinical audit can support safer, higher-quality care for conditions such as stroke.  Importantly too, the programme has evolved over time and with the evidence. For example, in 2024 the audit initiated its most substantial reform to date, reflecting the 2023 National Clinical Guideline for Stroke and NICE stroke rehabilitation guidelines – setting a renewed benchmark for what best practice should look like. These standards provide confidence and reassurance to both clinicians and patients that the most effective stroke care is being delivered.

Over recent years, patients have benefited from advances in imaging, increasing access to specialist treatments and progress in aspects of hyper-acute care. Yet challenges remain, including delays before hospital arrival and the need to strengthen long-term community support.

Looking ahead, SSNAP’s comprehensive data collection and timely feedback aligns closely with NHS England’s recently published Quality Strategy, by enabling the use of meaningful data to identify unwarranted variation, monitor outcomes, support continuous improvement and drive more equitable care. Providing actionable intelligence across the stroke pathway, the audit helps create the conditions for safer, more effective and patient-centred services, while supporting the NHS ambition to use data and digital tools to improve quality at scale.

“National clinical audit helps make challenges visible. By providing robust evidence about what is working, where gaps remain and how services compare across populations, SSNAP enables clinicians, providers and commissioners to focus improvement efforts where they can make the greatest difference. With World Patient Safety Day shining a light on patient safety for noncommunicable diseases, the message from stroke audit is clear: better evidence leads to better decisions, and better decisions help deliver safer care for patients.” Chris Gush, HQIP CEO

Further resources from HQIP

  • Discover more of our programmes, reports, and other resources and news related to neurology and stroke care.
  • More articles on using healthcare data to improve and save lives
  • How HQIP supports organisations to use clinical audit and healthcare data to drive improvement – from strategy development to implementation or training
  • Reports and infographics
  • Benchmarked results, searchable by project name, trust, hospital or unit

Seeking direction – Skills passport for clinical audit professionals

6 Sep 2026

Jack Hiscock, an NHS-based Clinical Audit and Effectiveness Coordinator and member of the HQIP-hosted National Clinical Audit and Clinical Effectiveness Collaborative (NCA-ACE), explains why he believes that a ‘skills passport’ for clinical audit professionals would deliver value for the healthcare sector, for patients and, of course, for the professionals themselves…

“In the current NHS environment, with increasing financial pressures, the need to professionalise clinical audit has never been more urgent. Establishing a structured progression pathway would help us standardise what should be expected of individuals working in our sector at different levels, including those moving into senior roles. It would also create clearer opportunities for people to gain experience and develop into recognised specialists within our field. One of the most effective ways to achieve this, I believe, is through the development of a ‘skills passport’.

Skills passports? What are those?

Skills passports are used widely across the healthcare sector, with clinical competency passports now either established, or being established in nursing, pharmacy, and allied health professions. They are also increasingly common outside healthcare – in fields such as archaeology and energy where they enable individuals to move between organisations while clearly demonstrating their suitability for a role.

There are, however, important differences between types of passports. Clinical skills passports tend to be highly explicit, with competencies broken down into discrete tasks that require formal sign‑off by trained and competent staff. This is not something we are likely to replicate in our sector, given the limited opportunities for formal qualifications and the nature of our work. Our skills are not always granular in the same way. For example, while many of us support colleagues in developing project proposals, these types of skill are not processes that can naturally be reduced to step by step, technical actions in the way that changing a drug giving set can.

As a result, our approach aligns more closely with the skills passports used in non‑healthcare sectors, which emphasise broader capabilities and areas of experience. This may be more beneficial, particularly as data‑focused roles continue to grow, where demonstrating experience in handling large datasets is often more meaningful than outlining the specific steps used to do so.

How might this look for us?

The mention of the archaeology skills passport given above is no accident. As someone who in a previous life (over 15 years ago) was in the archaeological sector just prior to the release of the Archaeology Skills Passport, I’ve seen how role expectation has become more consistent and supported by more structured workplace development. By aligning with professional standards produced by the Chartered Institute of Field Archaeologists, the passport provides a common framework for recording competencies, supports professional development, and can evidence progression towards professional accreditation.

By using a similar structure to the archaeology skills passport, with skills grouped from Primary through to Tertiary, we could start to map out the wider capabilities needed in clinical audit roles. Primary skills could be anchored to the HQIP four‑stage model which comprises preparation and planning, measuring performance, implementing change, and sustaining improvement. Relevant secondary and tertiary competencies could then be woven into each stage.

For example, the planning and preparation stage could include ‘understanding sources of projects’ – which could be further separated into learning around requirements for NICE compliance audits as well as audits that link in with national and regional priorities and strategies (such as the 10 Year Health Plan for England and NHS Quality Strategy).

As part of the measuring performance stage, acquisition of more hands-on skills could be demonstrated via apprenticeships in data analysis or via in-house Excel training offerings, dependent on your Trust’s development opportunities. The passport could also bring in learning on understanding coding as part of obtaining patient data, and understanding patient experience to assist with patient involvement in projects and programmes.

The implementing change stage may be a good place for Quality Improvement (QI) skills to fit into the passport. While some QI techniques are already commonly included in clinical audit roles (such as root cause analysis using fishbone diagrams and the 5-whys), others such as PDSA cycles and testing changes could also be aligned here.

Action planning and implementation following successful tests-of-change might better align with the sustaining improvement stage alongside continued measurement and re-audit.

Specific alignment of audit and QI skills may help to explain the relationship between them and better articulate how they work together across assurance and improvement.

Next steps

I’ve floated this idea before with colleagues in other Trusts, and the reaction has been mixed. The concern, understandably, is that a skills passport might lead to revisiting job bandings—especially if we begin mapping skills against banding levels or move toward more standardised job titles. That is a possibility. But given the current climate, where the number of clinical audit roles are shrinking and bandings are already being considered, it may be more important than ever to have a clear framework that evidences the skill requirements of our sector. Something that sets out what our roles involve, the skills we bring, and the experience we’ve built up.

And finally

In the end, we must look for ways that can help us give new colleagues starting out in this field a framework in which they can develop and get the most out of what can be a rewarding career in helping to improve care for patients and families. We also need to demonstrate the value of the experience we have developed – often over many years.  The skills passport is just one way that we can begin this journey.”

This article reflects the author’s personal perspective and is intended to prompt discussion among clinical audit and clinical effectiveness professionals.

Have your say

If you have would like to share your thoughts about Jack’s article, please do so on the NCA-ACE workspace on the NHS Futures platform (open to eligible professionals).

Further information about NCA-ACE

The National Clinical Audit and Clinical Effectiveness Collaborative (NCA-ACE) is a national forum for local NHS trust clinical audit and clinical effectiveness professionals, hosted by HQIP. Monthly virtual meetings feature guest speakers, thematic presentations, Q&A and shared learning. Members are supported through the NCA-ACE workspace on NHS Futures, with discussions and sharing of information and materials.

For more details about NCA-ACE, and details of how to join, email HQIP.

How AI Could Help Clinical Audits and Registries

27 Jul 2026

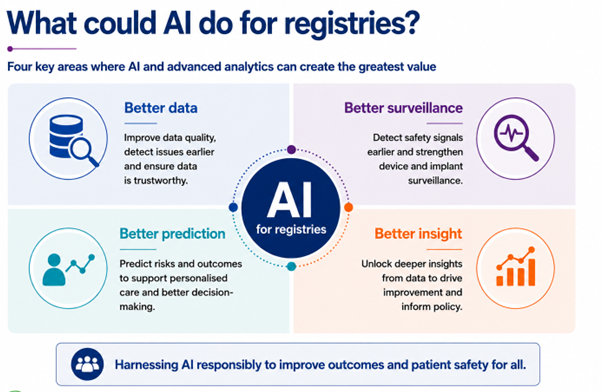
Artificial intelligence is hard to avoid at the moment. Every week seems to bring another announcement or new tool. While most of the attention has been on large language models like ChatGPT, AI covers a much wider range of technologies, many of which could have practical uses in healthcare.

As part of Clinical Audit Awareness Week 2026 (CAAW26), Chris Boulton, National Joint Registry (NJR) Director of Operations, looked at how AI could support clinical registries, where it has the greatest potential, and some of the challenges that still need to be addressed.

“Like many organisations, we’re trying to separate the genuine opportunities from the hype. AI is developing quickly, but that doesn’t mean every new idea will improve healthcare. Our job is to understand where it can make a practical difference and where existing approaches remain the better option.

The National Joint Registry (NJR), which is hosted by Healthcare Quality Improvement Partnership (HQIP), exists to improve patient safety by recording, monitoring, analysing and reporting the outcomes of joint replacement surgery. Since it was established in 2003, it has become the largest joint replacement registry in the world, holding more than 4.65 million procedure records and receiving around 250,000 new records every year.

That scale creates opportunities that simply didn’t exist a decade ago. The NJR already supports implant surveillance, clinical audit, research and quality improvement. As the volume of data continues to grow, AI offers another way of analysing that information and finding patterns that would otherwise be difficult to detect.

My CAAW26 presentation focused on a few key areas where AI could make the biggest difference.

Improving data quality

Good analysis starts with good data. Large datasets inevitably contain missing information, inconsistencies and records that need checking. Finding those records can take a lot of time.

AI could help identify records that deserve closer inspection. It may spot unusual coding patterns, unexpected combinations of values or anomalies that suggest something has gone wrong during data collection. That would allow data teams to focus their time where it is most needed.

Better insights

Clinical registries contain huge amounts of information, and much of the value comes from understanding how different pieces of that information fit together.

AI could help identify patterns and relationships that are difficult to spot using conventional analytical techniques alone. That could generate new insights into patient outcomes, implant performance and variation in practice, helping us ask better questions, focus future research and communicate findings more effectively to clinicians, patients and other stakeholders.

Improving surveillance

Monitoring implant performance is one of the NJR’s core responsibilities. The registry already uses established statistical methods to identify potential patient safety concerns. AI has the potential to add another layer by recognising patterns across millions of records and highlighting areas that warrant further investigation.

Any potential safety signal would still need careful statistical analysis and clinical review before conclusions were drawn, but AI may help identify those signals earlier.

Better prediction

One of the most exciting possibilities is using registry data to improve prediction. By analysing millions of procedures, AI may help estimate things like the likelihood of revision surgery, complications or recovery after an operation. As more data becomes available, those predictions have the potential to become increasingly accurate.

Better prediction gives patients and clinicians more information before decisions are made. It won’t remove uncertainty, but it can help people make better informed choices.

The same technologies could also make registry information easier to access and understand. That could include answering questions from patients, producing tailored summaries for clinicians or presenting information in a more accessible way.

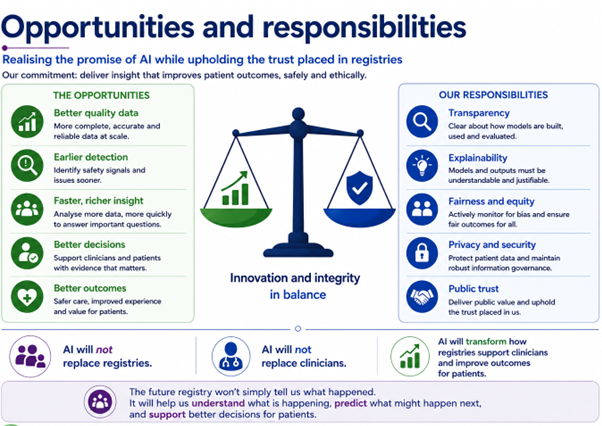
Governance and trust

Technology is only one part of the picture.

Any use of AI within the NJR has to be supported by strong governance, clear accountability and robust information governance. Patient confidentiality, cyber security and transparency remain just as important as they are today.

We believe AI models need to be properly evaluated, monitored and understood before they are used to interpret data. Public trust will be just as important as technical performance, and we want trust to be one of the guiding principles of the NJR’s AI strategy.

Developing the NJR’s approach

Earlier this year, we established an AI and Analytics Working Group, led by Professor Mark Wilkinson from the University of Sheffield, to help develop the registry’s AI roadmap. The group is bringing together clinicians, data scientists, academics and registry staff to explore where AI can genuinely add value, learn from organisations already working in this area and identify practical applications worth developing further. That includes improving analytics and surveillance, as well as supporting reporting, stakeholder communication and routine administrative tasks.

AI is moving quickly, and nobody knows exactly how it will change healthcare over the next decade. There will be plenty of new ideas, and not all of them will stand up to scrutiny.

For us, the priority is straightforward. We’ll continue exploring where AI can improve the registry, evaluate new approaches carefully and adopt them where they make a real difference. The aim is the same as it has always been: using high quality data to improve patient safety and support better care.”

Further resources from HQIP

  • Innovation webinar and other webinars from Clinical Audit Awareness Week 2026 – recordings and slides available
  • Discover more about how HQIP supports organisations to use clinical audit and healthcare data to drive improvement – from strategy development to implementation or training
  • Guidance and other resources to support improvement
  • Reports and infographics
  • Benchmarked results, searchable by project name, trust, hospital or unit

Audit, Registry and Outcomes Data: At the Heart of Strategic Commissioning

20 Jul 2026

Dr Iain Smith, HQIP Associate Director, Association for Clinical Audit, Registries and Quality Improvement (ACAR-QI), features in BMJ Leader Blog this month, on why audit, registry, and outcomes data must sit at the heart of strategic commissioning:

“Integrated Care Boards (ICBs) play a crucial leadership role in the English NHS. They are responsible for managing health systems across large geographical footprints and ensuring that services are planned and delivered to meet local population needs.1

The UK government’s new NHS modernisation bill confirms strategic commissioning, the process of planning, purchasing and monitoring services, as the central purpose of newly reconfigured ICBs.2–4 As ICBs move towards their role as strategic commissioners, they will focus on optimising resource use to improve population health; reduce inequalities; improve access to services; and deliver high quality outcomes for patients.2 3

To support ICBs in this role, is a strategic commissioning framework comprised of four key steps: understanding the local context; developing long-term population health strategy; delivering value-for-money outcomes; and evaluating impact of commissioning decisions.3

Key to success as a strategic commissioner is the need to demonstrate measurable outcomes and improvement. Clinical audit and registry data must therefore play a major role at the heart of strategic commissioning.

Clinical audit, registries and understanding the local context

Strategic commissioners must develop a deep understanding of their local population and its health and care needs.3 Clinical audit and registries provide condition and pathway specific data on care processes, outcomes, variation and inequalities across providers and geographies. Audit and registry data contribute benchmarked comparisons between local providers, ICBs, regions and national averages – helping commissioners identify where outcomes, access or care processes differ from expected standards.5 6

For example, reducing lives lost to cardiovascular disease (CVD) is an identified priority in the NHS ten-year health plan for England.7 CVDPREVENT is a national primary care audit using routinely extracted GP data to identify undiagnosed, undertreated or overtreated patients with high-risk cardiovascular conditions.8 This can support ICBs to understand population need, inequalities and prevention opportunities at place, neighbourhood and practice level.

Clinical audit, registries and developing population health strategy

Strategic commissioners need to develop evidence-based population health strategies that link health with broader socioeconomic outcomes to improve equity and support prevention.3 Strategies need to translate into outcomes that matter for patients, such as fewer heart attacks or strokes and effective care pathways.7

The National Audit of Cardiac Rehabilitation (NACR) supports planning of cardiovascular prevention and rehabilitation services by monitoring access, equity, quality and outcomes.9 Whereas, the Sentinel Stroke National Audit Programme (SSNAP) captures whole-pathway stroke data supporting long-term strategy for hyperacute stroke, thrombectomy and rehabilitation.10

Audit data and value-based healthcare

Strategic commissioners must prioritise funding and maximise value.3 Delivery of strategic outcomes will be supported through allocating resources informed by data and population health priorities. Metrics from audits and registries can be included in contracts and transformation programmes. For example: the National Emergency Laparotomy Audit (NELA) links improved outcomes with shorter length of stay and potential savings;11 the National Hip Fracture Database (NHFD) supports the best practice tariff for hip fracture care in England;12 and the National Joint Registry (NJR) shows continued reduction in revision surgery and improved outcomes.13

Clinical audit, registries and evaluating impact

Strategic commissioners need to monitor whether decisions improved outcomes, reduced inequalities, improved access and delivered value.3  Clinical audits and registries are designed to identify where care meets standards and where improvement is needed. They enable repeated measurement and can support quality improvement cycles.14 15 Registries capture longitudinal data, and many audits publish periodic data, allowing commissioned changes to be tracked over time.5  By using audit and registry data, commissioners can evaluate the impact before and after pathway redesign, investment or service reconfiguration.

Making it happen – access to data and linkage across datasets

Audit and registry data offer meaningful clinical process and outcome metrics. The data however can sit in different places – such as individual audit provider websites. Furthermore, for strategic commissioning, ICBs must consider activity, workforce and finance data – which can also sit in separate places.

Bringing datasets together supports a more rounded view of outcomes, safety, variation, equity, and value – not just lower cost. This points to an enhanced role for digital tools such as secure data environments (SDEs) and open access platforms such as National Clinical Audit Benchmarking (NCAB) and NHS Open Model Health System (OMHS).

NCAB provides benchmarked results from the National Clinical Audit and Patient Outcomes Programme (NCAPOP).16 OMHS provides benchmarked data on quality, productivity and outcomes, including from selected national clinical audits.17 Both NCAB and OMHS are open platforms providing benchmarked public data.17 18 This matters for strategic commissioning because ICBs are expected to make evidence-based, transparent decisions.

SDEs are platforms that control who can access data, what they can access, and what they can do with it. They allow approved users to work securely with de-identified data and enable access to health and care data for research and analysis.19 20 SDEs reduce the need for ICBs to negotiate bespoke data flows and make evaluation of commissioning decisions easier.

National clinical audits and registries can help ICBs move from broad strategic intent to measurable commissioning action – showing where need is greatest, where variation exists, and whether commissioned changes are improving outcomes equitably over time. Making audit and registry data available through SDEs and open access platforms would help ICBs use national audit and registry data as core strategic commissioning assets.”

This article was published as a blog on BMJ Leader on 20th July 2026: Audit, registry and outcomes data: At the heart of strategic commissioning. By Iain Smith – The official blog of BMJ Leader

Further resources from HQIP

  • Discover more about how HQIP supports organisations to use clinical audit and healthcare data to drive improvement – from strategy development to implementation or training
  • Guidance and other resources to support improvement
  • Reports and infographics
  • Benchmarked results, searchable by project name, trust, hospital or unit

References

  1. NHS England. What is integrated care? London, UK: NHS England; n.d. [Available from: https://www.england.nhs.uk/integratedcare/what-is-integrated-care/.
  2. Department of Health & Social Care. Health Bill: ICBs as strategic commissioners – fact sheet London, UK: UK Government; 2026 [Available from: https://www.gov.uk/government/publications/health-bill-icbs-as-strategic-commissioners-fact-sheet/health-bill-icbs-as-strategic-commissioners-fact-sheet.]
  3. NHS England. Strategic commissioning framework London, UK: NHS England; 2026 [Available from: https://www.england.nhs.uk/long-read/strategic-commissioning-framework/.]
  4. NHS England. Commissioning: NHS England; n.d. [Available from: https://www.england.nhs.uk/commissioning/.]
  5. NHS England. Clinical audits and registries: A best practice guide. London: NHS England (Available at https://future.nhs.uk ), 2026.
  6. NHS England. Clinical Audit London, UK; NHS England ;n.d. [Available from: https://www.england.nhs.uk/clinaudit/.]
  7. Department of Health & Social Care and NHS England. Fit for the future: 10 Year Health Plan for England. London: UK Government, 2025.
  8. CVDPREVENT. The Cardiovascular Disease Prevention Audit Derby, UK: NHS Arden and Greater East Midlands Commissioning Support Unit; n.d [Available from: https://www.cvdprevent.nhs.uk.]
  9. NHS England. National Audit of Cardiac Rehabilitation n.d. [Available from: https://digital.nhs.uk/data-and-information/clinical-audits-and-registries/national-audit-of-cardiac-rehabilitation.]
  10. Royal College of Physicians. Sentinel Stroke National Audit Programme (SSNAP) London, UK: Royal College of Physicians; 2017 [Available from: https://www.rcp.ac.uk/resources/sentinel-stroke-national-audit-programme-ssnap/.]
  11. Royal College of Anaesthetists. National Emergency Laparotomy Audit (NELA) London, UK: Royal College of Anaesthetists; n.d. [Available from: https://www.rcoa.ac.uk/research/research-projects/national-emergency-laparotomy-audit-nela.]
  12. Royal College of Physicians. The Fragility Fracture and Falls Audit Programme (FFFAP) n.d. [Available from: https://www.fffap.org.uk/FFFAP/Resources.nsf/.]
  13. NJR. National Joint Registry, London, UK: NJR; n.d. [Available from: https://www.njrcentre.org.uk accessed 29 Jun 2026.
  14. Smith I. Quality management and clinical audit: Integrating clinical audit and quality improvement to deliver impact for patients London, UK: BMJ Leader; 2026 [Available from: https://blogs.bmj.com/bmjleader/2026/02/09/quality-management-and-clinical-audit-integrating-clinical-audit-and-quality-improvement-to-deliver-impact-for-patients-by-iain-smith/.]
  15. Davey N, Shearer H, Matthew D, et al. Clinical audit and quality improvement: rivals, partners, or one and the same? Frontiers in Health Services 2026;Volume 6 – 2026 doi: https://doi.org/10.3389/frhs.2026.1768450
  16. HQIP. National Clinical Audit Benchmarking (NCAB) London, UK: Heathcare Quality Improvement Partnership; n.d. [Available from: https://www.hqip.org.uk/programmes-data/benchmarking/.]
  17. NHS England. Model Health System London, UK: NHS England; n.d. [Available from: https://open.model.nhs.uk.]
  18. HQIP. National clinical audit data features in open access NHS Model Health System London, UK: Healthcare Quality Improvement Partnership; 2026 [Available from: https://www.hqip.org.uk/news/open-mhs-launch/.]
  19. Department of Health & Social Care. Secure data environment for NHS health and social care data – policy guidelines London, UK: Department of health & Social Care; 2022 [Available from: https://www.gov.uk/government/publications/secure-data-environment-policy-guidelines/secure-data-environment-for-nhs-health-and-social-care-data-policy-guidelines.]
  20. NHS Digital. Secure Data Environments London, UK: NHS England; 2026 [Available from: https://digital.nhs.uk/data-and-information/research-powered-by-data/support-and-resources/background/secure-data-environments.]

Culture Follows Structure

19 Jun 2026

Structural change must come before cultural change in patient safety.

Professor Ted Baker, Chair of the Health Services Safety Investigations Body (HSSIB) and the Independent Advisory Group for the HQIP-hosted Medical & Surgical Clinical Outcome Review Programme, is a key speaker during Clinical Audit Awareness Week 2026; featuring in the Data-Informed Improvement: From Insight to Impact morning webinar on Friday 26th June 2026. In this article, he explains more about his presentation, and the lessons that can be learned from regulatory and safety bodies in using audit data for improvement.

The exhortation problem 

Read the recommendations of any major patient safety inquiry of the past thirty years and you will find, somewhere near the end, a call for cultural change. Each was followed by initiatives, frameworks, leadership programmes and organisational pledges to improve. And in each case, the same cultural failures have recurred, sometimes within the same organisations. 

This is not because those leading the initiatives were wrong or lacking in commitment. It is because culture cannot be changed by telling people to change. Culture is an emergent property of the structural conditions in which people work. Change those conditions and culture tends to follow. Leave them intact and culture reverts, regardless of how many training days, values statements or staff engagement programmes are deployed. Healthcare has spent the better part of three decades trying to change culture by exhortation while leaving the structural conditions that produce bad culture largely intact. The result is a system that generates the same inquiries, produces the same recommendations, and regularly experiences the same failures. 

Structural conditions 

By structural conditions, I mean something specific, the formal systems, accountabilities, processes and incentives within which clinical work takes place, who is responsible for what, how risks are identified and managed, how learning is protected and shared, and what behaviours the organisation rewards or sanctions in practice rather than in theory. 

During my time as Chief Inspector of Hospitals at the CQC, I visited hundreds of NHS organisations. The ones with the strongest safety cultures were not the ones with the most impressive values statements. They were the ones where accountability was clear, where risk was actively managed rather than defensively reported, where leaders asked hard questions rather than sought reassurance, and where staff genuinely believed that raising a concern would make a difference. Those are structural features, the conditions from which a genuine learning culture can grow. 

Where those conditions are absent, the culture of silence and self-protection is not a failure of values. It is a rational adaptation to the environment. Staff are not telling us something about their character when they stay quiet. They are telling us something about the system they are working in. 

What other industries learned 

Aviation, nuclear power and rail achieved transformative reductions in harm by building safety management into the formal structure of how organisations operate, and making those structures a regulatory requirement. A safety management system has four elements. Safety policy establishes clear organisational intent with named accountabilities at the most senior level. Risk management proactively identifies hazards and implements controls before harm occurs. Safety assurance checks that those controls are working honestly, not to produce comforting dashboards but to surface genuine risk. Safety promotion creates the culture of learning, honest reporting and continuous improvement. 

You cannot promote a culture of learning if risk management is not honestly identifying what needs to be learned from. You cannot promote a culture of candour if safety policy is vague about who is responsible when things go wrong. In aviation, a safety management system is a regulatory requirement without which an airline cannot operate.  

The healthcare gap 

Healthcare lacks an equivalent mandate, and the consequences are specific and observable. Accountability is unclear. When harm occurs, the system struggles to identify whether it was a policy failure, a risk management failure, an assurance failure or a cultural failure, because these functions are not clearly defined or owned. The result is the familiar pattern, inquiry, recommendations, partial implementation, and recurrence. Each inquiry attributes the failure, at least in part, to culture. None can fully explain why the structural conditions that produce that culture persist. 

Quality improvement and safety management are treated as separate activities. In many NHS organisations, QI sits in one directorate, clinical governance in another, risk management in a third. The feedback that would allow learning from one function to inform another is weak or absent. National audit findings sit in HQIP programme reports. Investigation findings sit in HSSIB reports. Incident data sits in local risk management systems. Nobody is consistently joining the dots. 

The implications for clinical audit are clear. Audit is, in SMS terms, a safety assurance function, but assurance in its fullest sense, not the production of evidence that things are as they should be, but the active search for evidence that they are not. A compliance-driven reading of audit asks whether care meets a standard. A learning-driven reading asks what the data reveals about where risk lies and where practice needs to change. Audit findings are only useful if organisations approach them in that second spirit, and if those findings flow into a risk management process with the accountability to act on them.  

Where those connections are absent, audit will often produce insight without impact. The data improves; the practice does not. 

Safety promotion is being asked to do the work the other three SMS elements should be doing. Staff are told to speak up, but risk management systems do not consistently act on what they say. Duty of candour is mandated, but the protected learning environments that make candour possible are not structurally secured. Freedom to Speak Up Guardians are appointed, but the conditions that determine whether speaking up is genuinely safe remain unaddressed. 

Transparency of outcomes has been pursued vigorously for twenty-five years, and with genuine results. But transparency without safe space produces disclosure without understanding. When organisations believe that poor data may trigger regulatory consequence, the rational response is to manage the data rather than engage honestly with what it reveals. Outlier signals are explained away. Accounts of what happened become performances designed to satisfy scrutiny rather than honest descriptions designed to generate learning. The structural protections that make honest disclosure possible, including the statutory safe space under which HSSIB investigations operate, are not a soft cultural indulgence. They are a precondition for the truthful accounting that a functioning SMS depends on. 

What a safety management system in healthcare would look like 

HSSIB has recommended a national initiative to develop safety management systems in healthcare as a regulatory requirement. The Dash review recommended developing a quality and safety management system. These commitments need to be made concrete. A healthcare SMS does not require inventing new concepts, the four elements map directly onto activities NHS organisations are already expected to perform. What is needed is coherent connection between those activities, with clear accountability for each element. 

Safety policy means named board-level accountability for safety and policies specifying what will happen when responsibilities are not met. Not a framework to aspire to, but an expectation to be held to. 

Risk management means proactive identification of safety risks, drawing on all available intelligence, audit data, investigation findings, incident reports, staff concerns, near-miss analysis. This is where national audit programmes belong, not just as benchmarking exercises, but as a source of risk intelligence. An organisation that receives an alert-level outlier notification should connect it to its risk register as part of its SMS. 

Safety assurance means genuine scrutiny that surfaces risk, not comfort-seeking assurance for boards and regulators. The alert and alarm distinction in audit outlier analysis belongs here. Alert-level signals belong in a protected learning space. local inquiry, honest discussion, improvement action, no immediate external sanction. Alarm-level signals belong in the formal accountability space. Using the same mechanism for both purposes destroys the learning function. As Onora O’Neill argued in her work on intelligent accountability, systems built on disclosure requirements rather than genuine communication produce organisations that appear fully accountable without being genuinely understood. Audit data is only as useful as the culture in which it is received, and that culture depends on whether organisations believe the purpose is to support learning or to trigger sanction. 

Safety promotion is the cultural element the other three make possible. Protected learning environments and statutory safe space, of the kind HSSIB operates, allow honest accounts of failure to be given without fear, not merely for staff wellbeing but for the integrity of the information the system depends on. Transparency of outcomes is necessary and valuable; but without a genuine learning space it produces reassurance rather than understanding, disclosure rather than insight.  

Co-development of recommendations with intended recipients ensures learning produces actionable change rather than compliance obligations. A national recommendations repository, connecting audit, investigation and incident analysis, ensures learning is shared across the system rather than siloed. 

An SMS is not a checklist of separate activities. It is a system in which each element supports the others. Remove any element, or leave the connections weak, and the system defaults to performance rather than learning. 

What is needed 

The NHS’s growing commitment to quality and safety management systems is welcome. The question is whether it will be backed by the structural mandate that makes it real, or whether it will become another framework sitting alongside the many others that already exist, adopted voluntarily by some organisations and ignored by others. 

Real structural change means defined SMS elements mandated across the NHS with clear board-level accountability for each; CQC’s regulatory framework mapped to those elements so that external assurance and internal safety management reinforce rather than duplicate each other; and protected learning environments, backed by statute where necessary, so that the honest accounts on which genuine learning depends can actually be given. 

What has been absent is the will to mandate the structure rather than merely encourage the culture. Culture needs a helping hand. The hand it needs is structural. The moment to build that structure, with a national plan committed to it and a regulatory framework that could embed it, is now. 

Clinical Audit Awareness week, hosted by the Healthcare Quality Improvement Partnership, HQIP, runs from 22-26 June 2026 this year – FIND OUT MORE: www.hqip.org.uk/caaw26 

Further reading 

Health Services Safety Investigations Body. Safety Management. HSSIB; 2025. 

Dash P. Review of patient safety across the health and care landscape. Department of Health and Social Care; 2025. 

O’Neill O. Accountability, Trust and Informed Consent in Medical Practice and Research’. Clinical Medicine 4.3 (2004):269–276

Patient safety article baker

Mapping dementia care: from variation to evidence-informed improvement

11 Jun 2026

The number of people living with dementia in the UK is estimated to be almost 1 million, with projections indicating that it could rise to 1.4 million by 2040*. For people living with dementia, the journey through health and care services is rarely straightforward. From first concerns about memory, through diagnosis, to care in hospital and beyond, multiple services are involved, and the way they connect can vary significantly. 

The latest service mapping work from the National Audit of Dementia (NAD) – which is run by the Royal College of Psychiatrists and managed by HQIP on behalf of NHS England and others- offers an important new perspective on this pathway. By examining how dementia diagnostic services are organised and delivered across England and Wales, it highlights not just where variation exists, but where improvement is most needed.  

What service mapping reveals 

The NAD service mapping exercise set out to understand how dementia diagnostic services are structured across the system, capturing how patients move between primary care, memory services, specialist assessment and follow‑up support. What emerges is a complex and highly variable landscape. The route to diagnosis is not consistent and the availability of investigations, treatment and support also varies between services. This variation is not simply organisational detail. It has real consequences for patients and carers: 

  • How quickly someone receives a diagnosis
  • What support they receive afterwards
  • Whether their care feels joined up or fragmented.

Mapping these pathways is therefore an essential first step in improvement. It allows the system to move from anecdote to evidence, identifying where differences are unwarranted. Dr Charlotte Deasy, Clinical Lead at NAD, expands on the value of audit in improving care further: “By measuring what is happening, we can advocate for improvement through service level, system-wide and policy changes.”

These NAD findings are reinforced by earlier work on Memory Assessment Services (MAS). The MAS spotlight audit showed that: 

  • Waiting times for diagnosis have increased
  • Access to assessment, imaging and post‑diagnostic support varies widely between services
  • Patients in more deprived areas can experience longer waits and reduced access.

Variation on this scale means that a person’s experience of dementia care can depend significantly on where they live. The service mapping work adds a new dimension to this understanding. It shows not only that variation exists, but how it is shaped by differences in service design, commissioning and data flows across the pathway. 

A wider system perspective: findings from the CQC 

The challenges identified through NAD data are also reflected in national regulatory insight. The Care Quality Commission (CQC)’s report, published in May 2025, highlights that people living with dementia often face: 

  • Delays in diagnosis and access to support
  • A lack of continuity once diagnosed
  • Variation in how well services understand and meet individual needs
  • Inconsistent communication with carers.

At the same time, further research published by the CQC in March 2026 is clear about what good care looks like. It should be: 

  • Person‑centred and coordinated
  • Shaped by the individual and their carers
  • Delivered by staff with the skills, training and time to respond effectively.

Taken alongside the NAD findings, this presents a picture of a system that understands the goal, but where delivery remains uneven. 

From diagnosis to hospital care: evidence of improvement 

While variation persists, the evidence also shows that improvement is happening. Within hospital settings, NAD continues to demonstrate the impact of sustained measurement and feedback. Between 2023 and 2024: 

  • Pain assessment increased from 92% to 98% of patients
  • Delirium screening increased from 87% to 92%
  • Carer‑reported experience improved, including communication and overall care quality. 

These changes are significant. They reflect improvements in areas that directly affect safety, recovery and patient experience. They also demonstrate the value of audit data not just in identifying problems, but in supporting change over time. 

National clinical audits – the largest programme of which in the UK is run by HQIP – measure care and share insights to improve and save lives. Data and outcomes from these audits help care providers to identify variation, trends and opportunities for improvement in the care and management of a range conditions. This, in turn, empowers clinicians and system leaders to focus resources where they can have the greatest impact. 

In the case of dementia, the impact of this data becomes most visible when it is used locally. At South Warwickshire University NHS Foundation Trust, audit findings led to the creation of a Dementia and Delirium Outreach Team, supporting ward staff to improve care. The results included: 

  • A 20% reduction in length of stay
  • A 10% reduction in discharge to long-term care
  • An estimated 1,608 bed days saved.

These are meaningful outcomes for both patients and the system, demonstrating how evidence can translate into tangible improvements in care and efficiency. 

The role of patient and carer experience 

Across all parts of the pathway, patient and carer experience remains central. Audit findings show improvements in communication and overall care, but also ongoing concerns about involvement, information sharing and consistency of care. This aligns with CQC findings that carers often feel under‑informed or are required to advocate on behalf of their relatives. Ensuring that these voices are heard, and acted upon, is a critical part of improvement. It ensures that changes to services are grounded in what matters most to those using them. 

Phil, a patient with Lewy body dementia, expands on this point: “There needs to be an emphasis on providing tailored services to meet local needs, to avoid a generic model that supposedly ‘fits all’ and, in fact, doesn’t meet the needs of those living with a diagnosis of dementia. This can only be achieved by those who plan and commission services engaging with those of us who live with the disease, so that services are based on people’s actual needs.” 

Audit insight 

Across diagnostic services and hospital care, improvement depends on a cycle of measurement, learning and action. The National Audit of Dementia is central to this cycle, bringing together data, insight and improvement support across the dementia pathway. And there will be further insight to come from the audit, giving the opportunity to use the evidence more systematically, reduce variation and ensure that high‑quality care is not the exception, but the standard. 

For people living with dementia, and for those who care for them, that is not simply a policy ambition. It is a necessity. 

*Source: NHS England 

Further information 

Dementia article

Mental health: Using evidence to improve care

5 May 2026

With one in four adults in England and Wales experiencing a mental health problem every year, and emergency referrals for young people in England rising by over 50% in just 3 years*, mental health is a national concern. The announcement of a national review of mental health services, led by NHS England’s Chair, is a significant and welcome moment for the system. It follows a broader conversation about how the NHS measures, learns from, and improves the care it delivers; one that HQIP has been contributing to directly, ensuring that the data we already have is the cornerstone of building an NHS that is Fit for the Future. Another recent article, Measure, Learn, Improve, sets out more specifically how HQIP-commissioned data and evidence (from the National Clinical Audit and Patient Outcomes Programme, NCAPOP), supports service improvement. Here, I apply that principle to mental health care…

Around one in five adults in England lives with a common mental health problem, and there were 2.8 million referrals to adult community mental health services in 2023/24. Yet compared to major physical health conditions, where large national audits on cancer and cardiovascular disease have generated rich, longitudinal datasets, the mental health evidence base, while growing, remains less comprehensive. Indeed, many working in mental health and the voluntary sectors argue it is an area where high-quality, systematic data collection has historically lagged behind need.

Through the NCAPOP, HQIP commissions and manages national mental health audit and clinical outcome review work on behalf of NHS England and the Welsh Government, with some programmes extending across all four UK nations. These programmes generate important evidence on quality, safety, outcomes and patient experience, and they produce practical, clinically-led recommendations grounded in real-world delivery. They do not cover everything. Areas such as depression, anxiety and community mental health care remain relatively under-served in national audit terms, and harnessing routinely collected data such as the Mental Health Services Data Set has proved technically challenging. But what we do have is substantial, and it matters. The data from these programmes has the power to transform mental health care in an efficient and sustainable way.

It is also worth noting that there are two parallel national reviews underway. Alongside the NHS England mental health review, the Department of Health and Social Care launched its own review in December 2025, covering mental health conditions, ADHD and autism. Both highlight a system that recognises the scale of the current unmet need and the urgency for reform, and both signal an opportunity for audit and outcomes data to shape what comes next.

As these reviews progress, there is a real opportunity to use the existing evidence base to align national priorities, reduce duplication, and focus improvement activity where it will deliver the most meaningful benefit for patients. We do not need to start from scratch. We already have mature national programmes producing evidence on access, safety, outcomes and patient experience. The opportunity is to use that intelligence systematically.

Our data – a rich, national source of evidence

The National Confidential Inquiry into Suicide and Safety in Mental Health (NCISH)

The Mental Health Clinical Outcome Review Programme, known as NCISH, is one of the Clinical Outcome Review Programmes commissioned by HQIP. Run by the University of Manchester, it provides internationally respected evidence on suicide and patient safety, examining suicide and homicide for people who have been in contact with mental health services, as well as sudden and unexplained deaths of psychiatric inpatients. The programme extends across England, Wales, Scotland and Northern Ireland.

Its annual reports and themed analyses provide recommendations at national and local level, directly informing suicide prevention strategy across all four nations. The programme has helped services better understand risks and opportunities for safer care, including through its widely cited ten key elements for safer mental health services.

The National Clinical Audit of Psychosis (NCAP)

The National Clinical Audit of Psychosis aims to ensure that everyone with psychosis receives high-quality, evidence-based care wherever they live. The programme is currently delivered by the Royal College of Psychiatrists, and covers all NHS-funded Early Intervention in Psychosis teams in England and Wales, providing a nationwide benchmark for the treatment and care that people with their first episode of psychosis receive.

Lived experience is central to how we approach that commissioning. Through ongoing engagement with service users and carers, we have heard clearly about delays in access to treatment, staff shortages and the variability of care across the country. Inconsistent care affects people’s ability to build meaningful relationships and find support in times of crisis. HQIP is committed to ensuring the audit’s priorities reflect those experiences, embedded in both the specification and how we monitor the contract. The most recent State of the Nation report was co-produced with clinical and service user advisors, a Service User and Carer Reference Group, and a steering group of over 30 clinicians, commissioners and NHS England staff. It found improvements in performance since the start of the audit in 2018/19 on the majority of the NICE quality standards, and highlighted key areas for improvement.

The National Audit of Eating Disorders (NAED)

Commissioned by HQIP in August 2024, the National Audit of Eating Disorders is a significant new addition to the national clinical audit portfolio. It seeks to drive improvement in the identification and appropriate management of eating disorders, and the quality and consistency of services for children and young people, adults of working age and older adults. A Service Mapping Report published in December 2025 drew on data collected from services across England, and achieved an outstanding 97% participation rate from eligible teams. Patient-level data collection commences in July 2026, with the first State of the Nation report due in July 2027.

The National Child Mortality Database (NCMD)

The National Child Mortality Database, which aims to reduce preventable child mortality, has produced some of the most widely cited work on child suicide in recent years. Its 2021 thematic report on suicide in children and young people identified 108 deaths assessed as highly or moderately likely to be due to suicide in a single year, equating to approximately two child suicides every week in England. Importantly, it also makes a number of important recommendations for suicide prevention. A full follow-up report drawing on cases since that publication is expected in 2027.

The Maternal, Newborn and Infant Clinical Outcome Review Programme (MBRRACE-UK)

The Maternal, Newborn and Infant Clinical Outcome Review, known as MBRRACE-UK, undertakes confidential enquiries into all maternal deaths from mental health-related causes. Mental ill health remains one of the leading causes of maternal death during pregnancy and in the first postnatal year, accounting for around a third of deaths, with substance misuse and other psychiatric causes among the leading factors. In April 2026, the Parliamentary Office of Science and Technology published a report on maternal mental health drawing directly on MBRRACE-UK’s findings, a clear signal that this programme’s evidence is shaping national policy conversations at a national policy level.

The impact of this work

The data and outputs from our national programmes are an invaluable, publicly available resource that shine a light on where improvements will have the maximum impact; supporting healthcare providers to implement changes that will improve not only mental health care but also outcomes and patient experience more widely. Alongside published reports, our impact reports and programme outputs bring together learning from across the system, highlighting where improvement is being made and where further focus is needed. Every project within NCAPOP has been established to address clinical areas where healthcare improvement is required. For mental health care, from suicide prevention and psychosis care to eating disorders and maternal mental health, that body of evidence is growing and becoming ever more important – in spite of the areas where gaps in national audit coverage remain.

What this means for national mental health care

With this robust body of evidence that is trusted by clinicians and patients alike, HQIP stands ready to support both the national mental health reviews and ensuring that clinical audit and outcomes data are central to shaping the next phase of mental health services. The evidence we hold is based on real-world findings; the programmes are active; and the findings are already being used, making a difference to patients’ lives. Trusts and other providers, and ICBs and regional clusters, do not need to wait for the completion of the reviews to act. Existing audit and benchmarking data can support local and national improvement now.

At the same time, HQIP is clear about what audit cannot achieve on its own. Improving mental health services at scale requires investment in data infrastructure, better use of routinely collected data, and a serious commitment to addressing the areas – including anxiety, depression, ADHD and autism – where the national audit evidence base remains insufficient. We call on those running these reviews to take the opportunity to join us in addressing this issue.

Our shared task is to ensure that the evidence generated across the system is used effectively, consistently and at pace to support improvement – and deliver mental health services that meet our growing need; leading to a population that is both healthier and happier than it is currently.

*Mind, May 2026

Further information from HQIP

Mental health article C Gush

Measure, Learn, Improve: Audit data and continuous learning in the NHS

15 Apr 2026

Across the NHS, clinicians and teams collaborate every day to provide safe, effective, and compassionate care. Drew Smith, HQIP Associate Director, argues that what turns this collective effort into a system that continuously learns and improves is not intention alone, but evidence…

Clinical audit and outcomes data provide that evidence. They allow us to see clearly how care is delivered, where variation exists, and what difference improvement efforts make over time. In short, successful learning and improvement are built on audit data, resulting in the most valuable of outcomes: improving and saving patients’ lives.

Interest in learning health systems is growing internationally as a means of solving problems and driving continuous improvement. In the UK, the Ten Year Plan for the NHS in England anticipates that “data will fuel continuous learning”. A learning health system is one in which data from routine care are systematically collected, analysed, and fed back to those delivering and planning services, creating a continuous cycle of learning and improvement. Audit and outcomes data sit at the heart of this cycle. They bring together high-quality, standardised data across organisations and care pathways to measure patient care against nationally-recognised standards.

What turns the NHS “into a system that continuously learns and improves is not intention alone, but evidence”

But at their best, audits do more than measure compliance with standards. They ask meaningful questions about quality: Are patients receiving the right care, at the right time, in the right place? Are outcomes improving, and are improvements experienced by everyone? Have changes to service delivery actually made a difference to what matters to patients?

Transparency is a critical mechanism through which audit data drive improvement. When data are fed back in a timely, accessible, and clinically credible way, they prompt reflection and dialogue. Teams can benchmark their performance, identify unwarranted variation, and learn from peers who are achieving better outcomes. Creating the conditions for curiosity and shared learning is as important as quality assurance.

Audit data also support improvement by enabling prioritisation. Health systems face constant pressure on time and resources. Robust outcomes data help leaders and clinicians focus improvement efforts where they will have the greatest impact for patients. They provide a basis for difficult decisions and help ensure that improvement activity is aligned with objective evidence rather than subjective assumptions.

“At their best, audits do more than measure compliance with standards; they ask meaningful questions about quality”

Importantly though, learning does not happen through data alone. It happens when data are interpreted in context and combined with clinical expertise, patient experience, and improvement capability. This is why projects commissioned by HQIP through the National Clinical Audit and Patient Outcomes Programme (NCAPOP), make quality improvement support available alongside measurement. Providing tools, case studies, and networks for shared learning helps translate insight into action and accelerates the pace of change.

For example, the National Audit of Care at the End of Life (NACEL) breaks the quality improvement journey down into six phases and signposts to resources at each stage. Alongside this, NACEL offers inspiration through an impact compendium and regular QI webinars.

Audit and outcomes data also play a vital role in addressing health inequalities. By disaggregating data by factors such as age, sex, ethnicity, deprivation, and geography, audits can reveal differences in access, treatment, and outcomes that might otherwise remain hidden. Making these differences visible is a necessary first step towards tackling them. A learning system is one that learns for all patients, not just the majority.

The pace of learning is another defining feature of a learning health system. NCAPOP audits are increasing the frequency with which data and quality improvement resources are made available, so clinical teams are able to test changes, see early signs of impact, and adapt more quickly.

“When we use audit and outcomes data wisely, we move closer to a health system that learns continuously”

Finally, audit and outcomes data help sustain improvement over time. One-off projects can deliver short-term gains, but without ongoing measurement it is difficult to know whether those gains have been sustained. Continuous audit provides a way to monitor progress, reinforce good practice, and adapt to new evidence or changing circumstances. To this end, many NCAPOP projects publish dashboards that track national and hospital performance over time, such as this dashboard on asthma in adults as part of the National Respiratory Audit Programme.

In the NHS, the ambition to become a learning health system is not abstract. It is rooted in the daily realities of care and the shared commitment to do better for patients. Audit and outcomes data give us the means to learn systematically from those realities. By investing in high-quality audits, focusing on meaningful outcomes, and supporting teams to use data well, we can create a virtuous cycle of measurement, learning, and improvement.

When we use audit and outcomes data wisely, we move closer to a health system that learns continuously – and one that delivers safer, more effective and more equitable care for everyone.

Further information 

Learning NHS article D Smith

A unique perspective: Seeing both sides of the story

7 Apr 2026

Meg uses her dual experience of maternity care and as a service user representative to explain why both patient voice and data must form the cornerstone of healthcare improvement.

Meg, who has been part of HQIP’s Service User Network (SUN) for a number of years, offers an interesting patient perspective. As an antenatal teacher in her professional life, she has a wealth of experience in maternity improvement at local, regional and national levels. So, with a ‘foot in both camps’, we were keen to know what Meg has to say about the value of patient voice and data in improving healthcare…

Her involvement began more than a decade ago with her local Maternity Services Liaison Committee, which later became a Maternity and Neonatal Voices Partnership. Over the years she chaired her local network, contributed to regional maternity systems, and participated in national projects centred on patient safety, coproduction and service improvement. This experience nurtured a deep belief that “healthcare can only improve when the people who use it are actively shaping it.”

The power of patient voice

As such, Meg is a long-time advocate for embedding service user voices into every layer of healthcare – from individual care experiences to national policy and audit. She summarises it simply: “understanding lived experience helps the system to ask the right questions, and avoids floundering in the dark.” Co-production, in particular, is something that Meg is keen to stress has many benefits for service providers and patients alike.

“Working collaboratively with patients to design services helps to get things right the first time, reducing costs and inefficiencies. It also ensures that people can access the right care in the right way, helping to address inequalities.” Importantly, Meg can see that it could play a key role in one of the biggest issues currently affecting healthcare: “By working together, we can identify risk early and prevent harm; particularly in areas like maternity, where safety concerns have been so prominent.”

The greater power of patient voice and evidence

This brings Meg to data. She feels that patient voice brings context to data, offering insight into what is happening ‘on the ground’. With patients involved in designing care, people “have trust in data and the decisions made,” she says. More generally, Meg stresses the value of using healthcare data when developing services, but suggests its value is more nuanced than that: “The true value of data lies in not only answering the questions we already have, but also in its ability to provide insights into the issues we never realised existed.”

The MBRRACE-UK maternal mortality findings loom large as an example. When looking at 2014-16 data, this HQIP-commissioned programme found that women from Black ethnic backgrounds had five times the risk of maternal mortality, compared to white women. After a national focus and targeted strategies, prompted by the data, the disparity was reduced to around double 2021-23. “Still unacceptable, but evidence of significant progress. But, without data it would still be five times – or worse!” Meg is keen to stress how widely trusted MBRRACE-UK data is, and how midwives, obstetricians and a variety of others working in maternity depend on it: “Its reliability and careful methodology mean it informs everyday clinical decisions as well as national improvements.”

From data to action

For Meg, collecting data is only the beginning. “We need to use it,” she emphasises – not just analyse endlessly. She points to the way that maternal mortality data has been translated into equity strategies across England’s ICBs, quoting the following examples:

  • More culturally competent care
  • Specific clinical conversations, such as guidance around vitamin D
  • Training to challenge structural and personal biases
  • Changes to how care is delivered in communities where risks are highest.

This, she says, is a powerful example of data “moving from spreadsheet to strategy to real-world change”.

The power of the SUN

Meg describes discovering HQIP during a period of postgraduate study in public health, and being drawn to the chance to broaden her involvement beyond maternity. The idea of contributing to work that cuts across healthcare appealed to her. What she found confirmed her hopes. “Voices are constantly being asked for,” she explains. “It feels like a genuinely embedded part of HQIP’s work.” Knowing that service user perspectives are both sought and meaningfully included has built her trust in the outputs – even for projects she hasn’t personally worked on.

Since joining the HQIP ‘s Service User Network (SUN), Meg has taken part in a wide range of activities, including:

  • Judging the HQIP Clinical Audit Awards, which allowed her to see outstanding practice in diverse areas such as patient safety and sustainability
  • Inputting into audit development and contributing to national audit work
  • Speaking to clinicians and stakeholders about coproduction, helping reinforce why it matters and how it can transform services.

Across these experiences, Meg emphasises how valuable it is to work with a well-run, responsive network. One of the strongest positives she identifies is the absence of tokenism. “It feels meaningful,” she says. “It’s not a tick-box exercise.” Knowing that her contributions will influence real work and real outcomes gives her a sense of purpose. Meg also stresses the wider societal benefit: “involving people with lived and diverse experiences helps to ensure that healthcare is genuinely usable, equitable and trustworthy.”

In terms of challenges, she raises one note of potential concern: namely, the need for audits to steer clear of ‘political’ influence. While she acknowledges that this is common across many sectors, she emphasises how crucial it is – especially in healthcare – for audit voices to be able to tell the full story: “otherwise the system risks missing opportunities to prevent harm.”

Looking ahead to the future

Meg is hopeful about the progress that has been made through a combination clinical audit and patient engagement, in maternity and beyond. However, she is cautious about repeated cycles of inquiries, saying that there needs to be an equal emphasis on acting quickly with what is already known.

But her overall message is clear: service user involvement, high quality audit and meaningful use of data are all fundamental to safer, more equitable and more compassionate healthcare. And she believes networks like HQIP’s SUN are crucial to making that happen.

Further information

National Cancer Plan: Opportunity for change

2 Mar 2026

A catalyst for working together to deliver a step change in improvement.

A step change in cancer care will only happen if we act as one system, and make the very best use of our national clinical audit and outcomes data. Now the dust has settled following the release of the Government’s National Cancer Plan for England, HQIP’s Medical Director Professor Danny Keenan, offers some reflections on its importance in improving care and outcomes for those with cancer, and on the importance of working together and making the most of data, to deliver its aims…

“The National Cancer Plan is very timely and will be well received. We have already been consolidating activities related to cancer care, but now is the time to make a step change and improve the key indicators of long-term outcomes for all patients.

The building blocks are in place. We are surrounded by standards related to most cancers. In terms of clinical audit to measure against these standards, we now have structural, process and outcomes measures for many of the most common cancers (see the list of national cancer audits at the end of this article). However, we need to take this further. This is where the Cancer Plan will help. The areas where we can focus our efforts on working together, to deliver its aims, are:

Earlier diagnosis

This will not be solved by one sector, such as primary care, working alone, but by all areas contributing. The NHS Ten-Year Health Plan for England has placed great emphasis on the “Left Shift”. This is the move to collaboration between sectors, ‘knocking down the walls’ of hospitals, and all working together between sectors to move expertise to where it benefits patients most – so that they have the best experience of care. In relation to early diagnosis, this means the different sectors combining into a more seamless service and reaching out to the population to drive improvement.

This is where the other tool that is available to us comes in, Cancer Alliances. We already have strong alliances in place, and we need to capitalise on their strengths so that they, working between sectors (as they currently do), help to seek out and bring forward patients to tackle the problem of late diagnosis.

Following the data

The improvement that follows from audit and reviews of service, to understand how to help providers that are performing less well, should play a fundamental part in this step change in cancer care.

We have, with the increased funding into the cancer programme, more and extremely useful information concerning the performance of the sector. We need to capitalise on this excellent information. It needs to be more widely disseminated, and we need to address the “so what” question more aggressively.

To disseminate this information more widely is important. It needs, particularly, to be made available in easy-to-use formats to front-line clinicians. Colleagues absorb information in diverse ways, and therefore several mechanisms need to be used. Using dashboards, designed to be used with minimum fuss, alongside social media and traditional media are all important.

To address the “so what” question, the Cancer Plan uses quite strong language. While we all agree that we need to tackle “eradicating variation”, this needs to be managed in a supportive way. All clinicians are working flat out, and we need support to work more cleverly not harder. That is where we, with the National Clinical Audits, can help. Those who provide the audits can develop quality improvement messages and tools that clinicians can use in their day-to-day work, driving improvement in the services that they offer. That will lead to reduced variation and eventually to improved outcomes.

This is another area where the Cancer Alliances can help. They are in the best position to influence clinicians and drive many of these quality improvement initiatives flowing from the National Clinical Audit programme.

The Cancer Alliances also have a role in bringing patient voice to the forefront. We need to ensure that their voice is centre stage as we develop services. The “Left Shift” is likely to be applauded by patients, but they need to understand why and how any change is taking place – and that it is there to improve their experience of care, as well as improve outcomes.

Cancer is cancer

Finally, I want to make a point about what the Cancer Plan calls “rare cancers”. That is an unhelpful term, in my view. If you were unlucky enough to suffer from one of these, you would not feel that its likelihood of occurring is relevant. You would expect exactly the same treatment and support as anyone with a “mainstream cancer”. There are a multitude of audits and registries assimilating data on these cancers with little support nationally. The information is therefore variable. However, we need excellent data on these cancers, as we do with others. HQIP can help here, through the development of an Association of Clinical Audits and Registries (ACAR). We could use our knowledge and skills to support these registries and audits to maintain excellent governance, and ensure that the service and information that patients receive are second to none.

In summary, we in HQIP appreciate the National Cancer Plan for England. We look forward to working with a wide spectrum of colleagues, and with patients, to work collaboratively to use data to implement it. National clinical audits are the backbone of accountable improvement in cancer care, while Cancer Alliances are built to deliver change across pathways. Now is the time to use both with greater ambition. It is not enough to measure variation. We must translate insight and collaboration into action that improves care, and supports teams to make progress with the time and capacity they have.

If we can bring all this together then I, for one, can see that the National Cancer Plan for England will take us a (significant) step closer to vast improvements in cancer care and outcomes for everyone.

National cancer audits

HQIP-commissioned cancer programmes, all within the National Cancer Audit Collaborating Centre (NATCAN), are:

Patient Perspective: Why Patients are the Route to Real Results

12 Feb 2026

Patient representative, Sadia, tells us why patient voice and data must shape healthcare improvement.

When Sadia first came across HQIP’s Service User Network (SUN), she wasn’t particularly looking for a new commitment – but she was keen to make a difference. Having taken part in patient engagement activities for a local research initiative previously, she was ready to contribute to something broader; something that would have national impact. What she found was a community where her voice – and the voices of people like her – could help shape the quality of healthcare across the country for everyone. Here she explains why patient involvement is important, and why it goes hand in hand with sharing healthcare data.

“When I saw the SUN network, it sounded exactly what I was looking for.” What stood out to her first was the tone of the advert: welcoming and flexible. “It said I could be involved as much or as little as I wanted. That really reassured me; it meant that I could contribute as and when I was able.” She signed up immediately. It was the beginning of a relationship that brought benefit to HQIP’s programme of national clinical audits as well as wider healthcare. It was also a relationship that saw Sadia develop her understanding of the value of patient voice, and the use of data, in changing healthcare for the better.

Why patient voice matters

For Sadia, the case for involving patients in healthcare improvement is simple and powerful. “We’re the ones receiving the care. We’re the only ones who can tell you if it’s working or not.” She has seen first-hand how involving patients early can prevent problems later on, and save time and effort. “If you include patients in discussions around care initiatives, they’ll spot issues before you roll them out – and they’ll help you to fix them. It makes care relevant, more efficient, and ultimately supports staff too.”

Improving care for everyone

Sadia, who has premenstrual dysphoric disorder (PMDD, a condition that took 12 years to be diagnosed), speaks candidly about her healthcare journey. As a British-South Asian woman under 30, she has faced many assumptions about her and her care. But change, she says, is happening. In her case, she connects this directly to women’s involvement. “When I was growing up, most research was done by men, for men, about men. Now we’re seeing much more research led by women, and that is focused on women’s health – and the involvement of female patients has played a key role too.” She believes that change has been possible in part because patients have demanded to be part of the solution: “We go through this, you should be studying us with us.”

Today, when she visits her doctor, they immediately know what PMDD is and what emerging treatments are being explored. “It gives me hope. Five or ten years ago, that wouldn’t have happened, and I’m grateful – not just for me, but for all the others with my condition.”

How data shapes better care

Sadia is open about once feeling hesitant about consenting to sharing her health data. “Healthcare hasn’t always focused on people like me, so I was unsure if it would be of benefit. But, through being involved with HQIP, I can see that sharing [anonymised] data is an important part of creating better services and outcomes.” For her, data and patient voice are equally important: “You need both to understand how care is working and where improvements are needed.” She also sees data sharing as essential to equity. “If someone like me doesn’t share my data, there won’t be relevant information to shine a light on conditions that affect people like me.”

What does patient engagement mean in practice?

Since joining HQIP’s Service User Network (SUN), Sadia has taken part in a wide range of activities, including reviewing reports, contributing to the development of resources, speaking at conferences, and generally offering insights based on both her personal experiences and those of people for whom she cares. “My father has cardiovascular disease, and I have been able to contribute, not just as a patient but also as a carer. Being able to bring that perspective into a meeting, and see it valued, was fantastic.”

The variety of opportunities is something she genuinely appreciates. “I feel like I’ve only touched the surface, in terms of what I could get involved in. But the great thing is, if you aren’t selected for one opportunity, another comes along quite soon. It is always very rewarding.”

A shared journey to continuous improvement

While Sadia says that she wouldn’t have chosen to go through the healthcare journey she has, she recognises that it does put her in a unique position of being able to benefit others, through patient engagement. “It did lead me to something meaningful,” she reflects. She is comforted that she is helping to shape a healthcare service that listens, learns, and improves.

For HQIP, Sadia’s story embodies exactly why patient involvement is critical for patient-centred, evidence-informed improvement in care. It deepens understanding. It ensures relevance. And, ultimately, it leads to care that meets the needs of real people. Or, as Sadia puts it: “If you’re listening to your patients, you’re going to get things right more often.”

Further information